
Is Air Embolism a Risk When Using Standard IV Sets?
Is there a risk of air embolism with standard IV sets? Yes, but the practical risk depends on device design, clinical setup, infusion conditions, and staff adherence to safe procedures.
For most routine peripheral infusions, properly primed and correctly monitored standard IV administration sets can be used safely when appropriate safeguards are consistently applied.
However, air embolism remains a relevant patient-safety concern because small process failures can combine with pressure differences, incomplete priming, open connections, or interrupted supervision.
Hospital procurement teams should therefore evaluate IV sets as part of a wider infusion safety system rather than treating them as simple, interchangeable consumables.
Clinical engineers, nursing leaders, distributors, and purchasing departments need to understand where air enters a fluid pathway and which product features reduce operational risk.
This article explains the real risks associated with standard IV sets, the safeguards that matter most, and the practical questions buyers should ask suppliers.
When Does Air Embolism Become a Meaningful IV Infusion Risk?
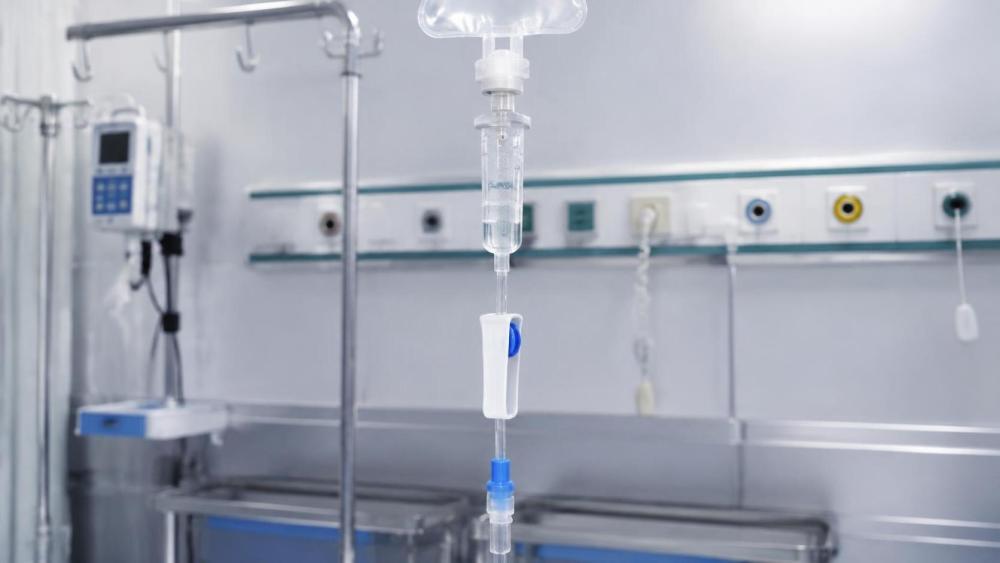
An air embolism occurs when air enters the vascular system and travels through circulation in a quantity or location capable of causing clinical harm.
The risk is not identical across all patients, access routes, infusion methods, and care environments. Peripheral IV therapy generally presents different exposure conditions than central venous access.
Air can enter through an incompletely primed administration set, an empty IV bag, a loose connection, a damaged component, or an incorrectly managed secondary infusion.
Pressure differences are especially important. Negative venous pressure, elevated infusion containers, patient positioning, or open central venous catheters can increase the possibility of air entry.
In routine gravity infusion through a peripheral cannula, very small residual bubbles often do not create the same clinical concern as larger volumes entering central circulation.
That distinction should not encourage complacency. The objective is to prevent avoidable air entry rather than rely on assumptions about harmless bubble size.
Air embolism can be difficult to quantify as a procurement risk because incidents may be rare, underreported, or related to multiple procedural factors.
For buyers, the correct question is not whether a standard IV set can ever be associated with air embolism. It can.
The more useful question is whether the selected set supports reliable priming, visible inspection, secure connection, predictable flow control, and appropriate clinical monitoring.
Why Standard IV Set Design Still Matters
Standard IV sets are often purchased based on price, packaging configuration, drip factor, tubing length, and connector compatibility. These specifications matter, but safety-oriented details also deserve attention.
A basic administration set typically includes a spike, drip chamber, tubing, roller clamp, injection port, distal connector, and sometimes a filter or needle-free component.
Each component can affect how easily staff prime the set, identify fluid levels, manage flow, and detect visible air before it reaches the patient.
A transparent, adequately sized drip chamber supports visual confirmation of fluid movement and helps clinicians maintain an appropriate fluid level during gravity infusion.
If the drip chamber is difficult to fill, poorly visible, or unstable during handling, staff may face unnecessary challenges during setup and routine checks.
Tubing material and internal diameter influence flow characteristics, flexibility, visibility, resistance to kinking, and the ease with which trapped air can be recognized.
Clear tubing is valuable because it allows direct observation of bubbles, fluid continuity, and potential backflow. Visibility is a practical safety feature, not merely a cosmetic preference.
Roller clamps should provide consistent control without sudden slipping, excessive stiffness, or unintentional reopening. A weak clamp can create downstream safety and workflow problems.
Secure luer connections, preferably aligned with recognized connector standards, reduce the chance of disconnection or leakage that may introduce air into the infusion pathway.
For procurement teams, these details should be translated into supplier evaluation criteria rather than left as informal preferences expressed by end users.
What Priming Procedures Prevent Most Avoidable Air Entry?
Correct priming is the primary defense against air delivery through a standard IV set. The process should remove visible air from the spike, chamber, tubing, ports, and connectors.
Staff should inspect the package before use, confirming that the sterile barrier is intact and that the administration set has no visible damage or manufacturing defects.
After inserting the spike into the fluid container, clinicians should fill the drip chamber according to the manufacturer’s instructions, usually to an appropriate partial level.
The roller clamp is then opened gradually to allow fluid to displace air throughout the tubing. The distal end should remain controlled during this procedure.
Any visible air should be cleared before connection to the patient. Attention is required around injection ports, extension lines, needle-free connectors, and filter housings.
Staff may need to tap components gently or reposition the tubing where bubbles adhere to internal surfaces. This should follow local policy and product instructions.
Priming should be repeated when an administration set is replaced, a line is opened, a secondary line is connected, or the fluid pathway is otherwise interrupted.
Procurement decisions should account for how easily a set can be primed during real clinical conditions, including emergency care, low-light settings, and high workload periods.
Usability testing with nurses can reveal problems that may not appear in a technical datasheet, such as poor chamber visibility or difficult-to-operate clamps.
Training remains essential because even a well-designed set cannot compensate for incomplete priming, rushed setup, or failure to inspect the line before patient connection.
Are Air Filters and Air-Eliminating Features Necessary?
Some infusion systems include air filters, air-eliminating filters, hydrophilic membrane filters, or pump-based air-in-line detection. These features may improve safety in selected clinical applications.
They should not be treated as universal substitutes for correct setup. Filters have flow limitations, compatibility requirements, priming instructions, and replacement considerations that must be understood.
An air-eliminating filter may help stop certain air volumes from passing downstream, but its performance depends on orientation, fluid characteristics, flow rate, and approved use conditions.
For example, some filters are intended for particulate filtration, while others are designed to manage air. These functions should not be assumed to be identical.
Infusion pumps may offer air-in-line alarms, which can provide an additional safety layer. Yet alarm sensitivity, tubing compatibility, and staff response procedures remain important.
Gravity infusion sets generally depend more heavily on correct priming, visual inspection, chamber management, and routine observation because they may lack automated air detection.
Higher-risk patients or therapies may justify enhanced safeguards. Examples can include central venous infusion, pediatric care, critical care, chemotherapy, parenteral nutrition, and pressurized infusions.
Buyers should determine whether these clinical areas require a different product category rather than expecting a low-cost standard set to meet every risk profile.
The correct specification is based on clinical risk assessment, not on the assumption that more features always provide better value in every ward.
How Should Hospitals Evaluate Standard IV Sets Before Procurement?
Hospitals should define a structured evaluation process that combines clinical requirements, technical performance, regulatory documentation, supply reliability, and total operating cost.
Start by separating routine gravity infusion needs from specialized applications requiring filters, extension sets, pump compatibility, pressure resistance, or enhanced air-management controls.
Procurement teams should request complete product specifications, including tubing dimensions, drip factor, chamber volume, connector type, filter details, sterility method, and material composition.
They should also verify applicable regulatory status in the intended market, labeling requirements, instructions for use, traceability information, and manufacturer quality-system credentials.
Documentation should clearly state the intended use, contraindications, storage requirements, single-use status, and disposal instructions. Ambiguous instructions can become a frontline safety issue.
Clinical evaluation samples should be tested by representative users, including nurses from inpatient wards, emergency departments, operating rooms, oncology units, and intensive care settings.
During product trials, teams should assess priming time, bubble visibility, drip chamber handling, roller clamp performance, connector security, tubing kinking, and compatibility with existing equipment.
Feedback should be captured in a consistent scoring framework. Informal preference alone can overlook important differences in workflow safety and product reliability.
Purchase price should be evaluated alongside waste rates, staff time, training needs, supply continuity, complaint history, replacement availability, and the cost of handling failures.
A marginally cheaper IV set may create higher overall cost when it increases setup difficulty, produces more unusable units, or requires frequent staff intervention.
What Questions Should Distributors Ask IV Set Manufacturers?
Distributors need product knowledge that extends beyond catalogue specifications. Their customers may expect guidance on selection, compatibility, handling, storage, and documentation readiness.
Manufacturers should be asked how the product is validated for priming, flow performance, tensile strength, leakage resistance, particulate control, and connection security.
It is also useful to ask whether the set is compatible with common IV fluids, lipid emulsions, blood components, contrast media, infusion pumps, and needle-free connectors.
Not every standard IV set is suitable for every fluid or therapy. Material compatibility and approved use conditions should be established before commercial claims are made.
Distributors should request complaint-handling procedures, post-market surveillance processes, product recall communication plans, and local technical support arrangements from their suppliers.
Packaging quality deserves review because crushed drip chambers, deformed roller clamps, compromised pouches, or unclear labels can create practical problems before clinical use.
Reliable supply is another safety consideration. A hospital forced to change IV set types repeatedly may face additional training burdens and increased variation in routine practice.
For tender submissions, distributors should prepare clear comparison tables that explain safety-relevant features without making unsupported clinical claims about embolism prevention.
Strong distributor support includes helping customers match the appropriate IV set to the application, while directing clinical decisions to hospital policies and qualified professionals.
Where Do Training and Workflow Controls Fit?
Even the best-designed IV administration set depends on competent use. Air embolism prevention is partly a device issue, but it is equally a process discipline issue.
Hospitals should maintain clear procedures for line priming, connection checks, bag replacement, secondary infusion setup, pump use, line tracing, and escalation of suspected defects.
Staff should be trained to inspect the entire fluid path before initiating infusion, not only the section closest to the IV bag or pump.
Routine checks should confirm that the container has not run dry, the drip chamber contains fluid, the tubing remains secure, and no unexpected air is visible.
Particular attention is needed during handovers, patient transfers, transport to imaging, emergency interventions, and changes between gravity and pump-assisted infusion methods.
Clinical engineering teams can support safe practice by maintaining infusion pumps, confirming compatibility lists, reviewing alarm performance, and investigating recurring device-related complaints.
Incident reports and near-miss reports should be analyzed for patterns. Repeated issues with one set type, connection method, or ward workflow may reveal correctable system weaknesses.
Procurement teams should include post-purchase monitoring in their plan. Product selection is not complete when a contract is awarded and stock is delivered.
Conclusion: Standard IV Sets Are Safe Only Within a Controlled System
There is a risk of air embolism with standard IV sets, but the risk is generally manageable when suitable products, correct priming, secure connections, and disciplined monitoring are combined.
For routine peripheral infusions, standard sets can support safe care when they are selected for the intended application and used according to validated instructions and local policy.
Higher-risk therapies, central venous access, pressure-assisted delivery, and vulnerable patient groups may require additional safeguards such as pump alarms, filters, or specialized administration systems.
Hospital buyers should evaluate IV sets through a patient-safety lens that includes usability, visibility, compatibility, documentation, supplier support, and performance under real clinical conditions.
For distributors and manufacturers, clear technical evidence and practical training support create more value than generic claims about safety or product quality.
The strongest procurement decision is one that recognizes IV administration sets as part of a complete infusion workflow, where product design and human practice must work together.